Why Some Tumors Are 'Cold' to the Immune System, and What That Means for Treatment
Inside the biology of immune-cold tumors, why checkpoint immunotherapy often struggles against them, and the research aimed at changing that
Key Takeaways
- •Tumors are classified as 'hot' or 'cold' based on how many T cells, the immune cells capable of killing abnormal cells, are present inside them.
- •Denser, well-positioned T-cell infiltration has long been linked to better outcomes, as shown by the Immunoscore system developed from colorectal cancer research.
- •Checkpoint immunotherapy works by releasing a brake on T cells that are already present, so it tends to work better in hot tumors than in cold ones.
- •Tumors with more genetic mutations often produce more neoantigens, unique markers that can help the immune system recognize and respond to cancer cells.
- •Some tumors actively block T cells from entering through mechanisms such as abnormal internal signaling, loss of surface markers needed for recognition, or physical tissue barriers.
- •Pancreatic and metastatic prostate cancers are commonly cited examples of cold tumors, each shaped by its own combination of low mutation burden and immune suppression.
- •Hot and cold describe the ends of a spectrum rather than a strict either/or category, with many tumors falling into intermediate patterns.
- •Converting cold tumors into hot ones through combination treatments remains an active research area, not yet a standard part of cancer care.
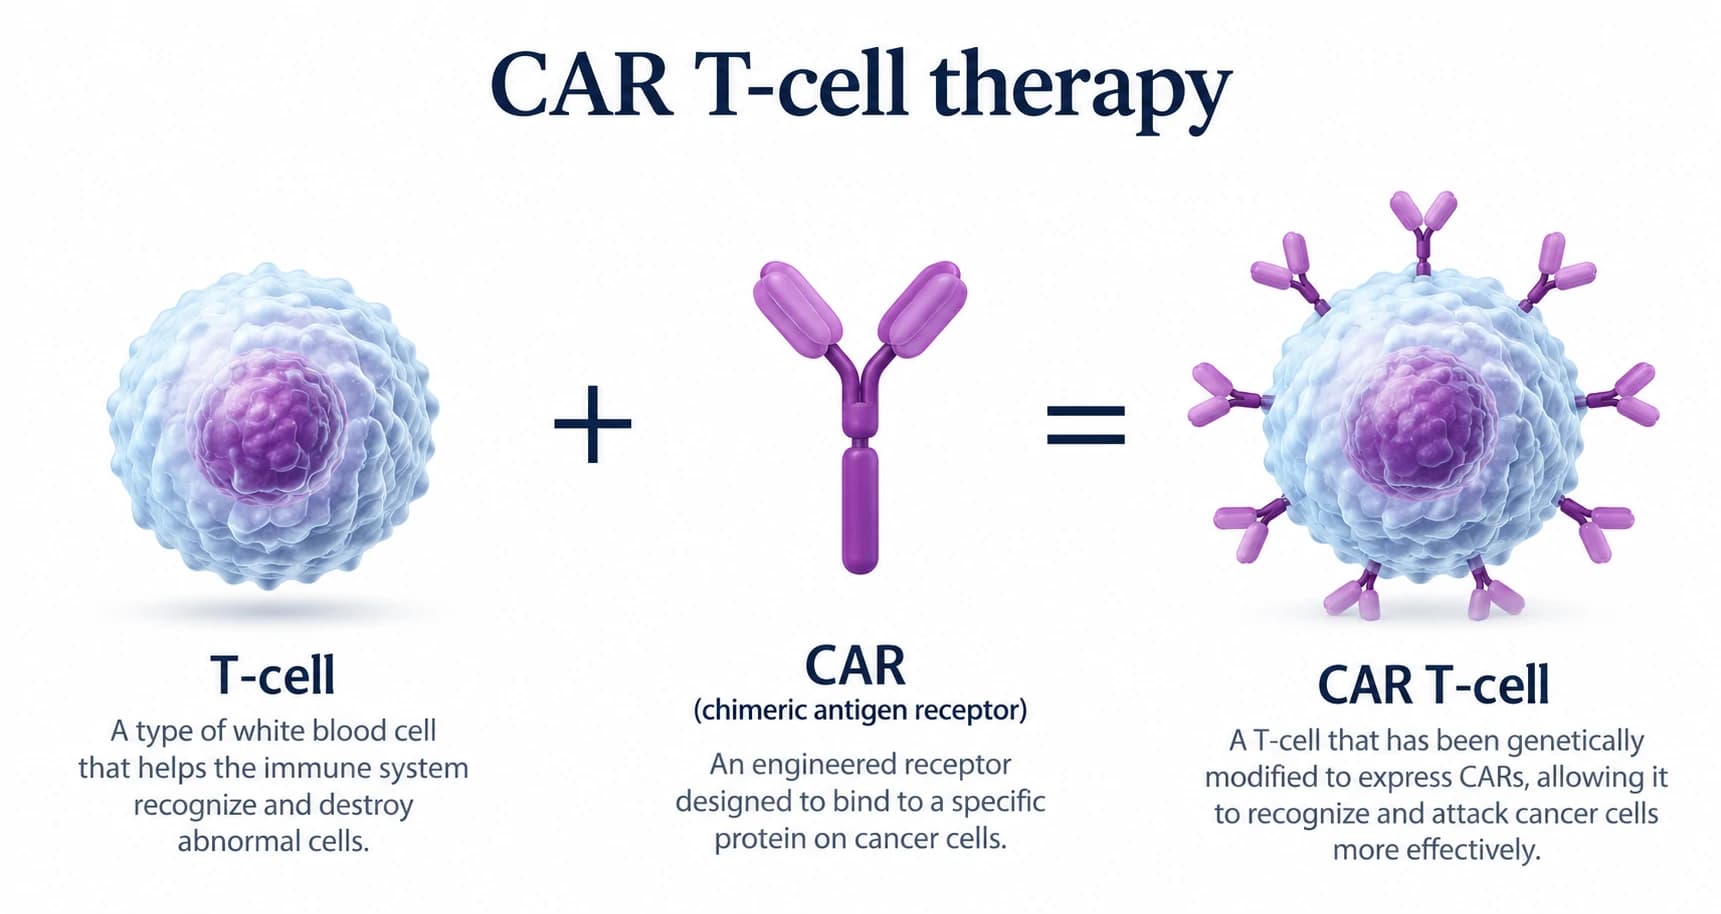
A tumor is not just a lump of cancer cells. It sits inside a mix of blood vessels, connective tissue, and immune cells that researchers call the tumor microenvironment. How many immune cells show up inside that environment, especially a type called T cells, turns out to matter enormously for how a cancer behaves and how well it responds to treatment.
Oncologists now sort tumors loosely into two groups based on that immune presence. A "hot" tumor is packed with T cells that have already made their way inside, ready to act if given the chance. A "cold" tumor has few or none. Cold does not mean less dangerous. It means harder for the immune system, and for certain drugs, to even see.
What Hot and Cold Actually Describe
The hot/cold label comes from how heavily a tumor is infiltrated by cytotoxic T cells, the immune cells capable of directly killing abnormal cells. This framework groups tumors by their immune activity rather than by which organ they started in. Two tumors from the same organ, even from the same patient, can land in different categories.
Immune Cell Location Predicted Outcomes Before Immunotherapy Existed
Long before checkpoint immunotherapy became common, researchers noticed that the amount and placement of immune cells inside a tumor predicted how a patient would fare. A landmark study of colorectal cancer, led by Jérôme Galon, found that the density, type, and location of immune cells inside the tumor predicted clinical outcome, sometimes more reliably than standard staging. That work became the basis for a scoring system called Immunoscore, which rates tumors by how deeply T cells have penetrated, from the outer edge to the center. A tumor with dense T-cell presence throughout tends to behave less aggressively, regardless of how advanced it looks on imaging.
Why Checkpoint Immunotherapy Needs Something to Work With
Immune checkpoint inhibitors do not create an immune response out of nothing. They release a brake that was stopping T cells already present from attacking. That is why tumors with pre-existing T-cell infiltration tend to respond better to this kind of drug than tumors that are immunologically empty. Releasing a brake does little if no engine is running to begin with.
One reason some tumors start with more T cells involves how many mutations they carry. Cancer cells accumulate genetic changes as they grow, and some of those changes produce abnormal proteins called neoantigens, fragments the immune system can recognize as foreign. Tumors with a higher mutational burden tend to generate more neoantigens, giving T cells more to latch onto. Research in non-small cell lung cancer linked higher mutational burden to better response to PD-1 blockade, suggesting a noisier genetic profile can translate into greater immune visibility. That relationship is not absolute across every cancer type, but it helps explain part of why some tumors run hot.
How a Tumor Can Actively Keep Immune Cells Out
A low mutation count is not the only path to a cold tumor. Some tumors actively repel T cells even when neoantigens are available. In melanoma, researchers found that switching on an internal signaling pathway known as WNT/β-catenin caused tumor cells to stop producing the signals that normally draw T cells inward. Despite having recognizable markers present, these tumors kept the immune system from ever finding them, which is a different problem than simply having nothing worth finding.
Several other routes can lead to the same cold outcome. A tumor cell can fail to display its internal contents through surface markers called MHC molecules, effectively going unlabeled to patrolling T cells. It can stop releasing the chemical signals that normally summon T cells toward it. Dense, scar-like tissue can form a physical wall around the tumor, blocking entry even when immune cells are nearby. And certain immune cells can work against the tumor's own defenders, including some whose normal job is to calm down immune activity once it has done its work, and another population that suppresses immune responses more broadly. A single tumor can be cold for several of these reasons at once, which is part of why no single fix works for every cold tumor.
Cancers That Tend to Run Cold
Some cancer types are cold more often than others. Pancreatic ductal adenocarcinoma, the most common form of pancreatic cancer, typically carries a relatively low mutational burden and is surrounded by a dense, immunosuppressive layer of supporting tissue. Those features combine to make it one of the clearest examples of a cold tumor, and it generally responds poorly to checkpoint inhibitors used alone. Interestingly, research on long-term pancreatic cancer survivors found their tumors sometimes carried unusually distinctive, high-quality neoantigens, suggesting immune recognition is possible there too, just uncommon.
Metastatic prostate cancer shows a related but distinct pattern. It tends to have low T-cell infiltration alongside an immune environment that actively works against attack, which helps explain why checkpoint immunotherapy has had limited success there despite its success in other cancers.
A Spectrum, Not a Switch
Hot and cold describe two ends of a range, not two fixed boxes. Many tumors fall somewhere in between. One widely used framework divides tumors into four groups: hot tumors with T cells throughout; tumors where T cells gather at the tumor's edge but cannot get inside; tumors where T cells are present but neutralized; and genuinely cold tumors with almost no immune presence at all. The distinction matters for treatment design, because a tumor where T cells are simply stuck at the border needs a different approach than one where T cells never show up in the first place.
Can a Cold Tumor Be Made Hot?
If coldness comes from several different mechanisms, warming a tumor up probably requires more than one tool. Researchers are testing combinations: radiation therapy, which can damage tumor cells in ways that release new antigens and attract immune attention; oncolytic viruses, which infect and kill tumor cells while flagging the area as under attack; and immunotherapy paired with chemotherapy or targeted drugs, each chosen to address a different barrier. None of these combinations has become standard treatment for most cold tumor types. They remain active areas of clinical investigation, not routine options.
Being classified as cold does not mean a cancer is untreatable. Surgery, chemotherapy, radiation, and many targeted therapies work through mechanisms that do not depend on immune infiltration at all. The hot/cold framework explains one piece of why immunotherapy succeeds in some cancers and struggles in others. It is not a verdict on a patient's overall treatment options, and any individual classification should be interpreted by an oncologist alongside the rest of a tumor's biology.
Common Questions
References
- Daniel S. Chen, Ira Mellman (2017). Elements of cancer immunity and the cancer–immune set point
- Thomas F Gajewski, Hans Schreiber, Yang-Xin Fu (2013). Innate and adaptive immune cells in the tumor microenvironment
- (2006). Type, density, and location of immune cells within human colorectal tumors predict clinical outcome.
- Paul C. Tumeh, Christina L. Harview, Jennifer H. Yearley, I. Peter Shintaku, Emma J. M. Taylor, Lidia Robert, Bartosz Chmielowski, Marko Spasic, Gina Henry, Voicu Ciobanu, Alisha N. West, Manuel Carmona, Christine Kivork, Elizabeth Seja, Grace Cherry, Antonio J. Gutierrez, Tristan R. Grogan, Christine Mateus, Gorana Tomasic, John A. Glaspy, Ryan O. Emerson, Harlan Robins, Robert H. Pierce, David A. Elashoff, Caroline Robert, Antoni Ribas (2014). PD-1 blockade induces responses by inhibiting adaptive immune resistance
- Suzanne L. Topalian, Janis M. Taube, Robert A. Anders, Drew M. Pardoll (2016). Mechanism-driven biomarkers to guide immune checkpoint blockade in cancer therapy
- Naiyer A. Rizvi, Matthew D. Hellmann, Alexandra Snyder, Pia Kvistborg, Vladimir Makarov, Jonathan J. Havel, William Lee, Jianda Yuan, Phillip Wong, Teresa S. Ho, Martin L. Miller, Natasha Rekhtman, Andre L. Moreira, Fawzia Ibrahim, Cameron Bruggeman, Billel Gasmi, Roberta Zappasodi, Yuka Maeda, Chris Sander, Edward B. Garon, Taha Merghoub, Jedd D. Wolchok, Ton N. Schumacher, Timothy A. Chan (2015). Mutational landscape determines sensitivity to PD-1 blockade in non–small cell lung cancer
- Stefani Spranger, Riyue Bao, Thomas F. Gajewski (2015). Melanoma-intrinsic β-catenin signalling prevents anti-tumour immunity
- Vinod P. Balachandran, Marta Łuksza, Julia N. Zhao, Vladimir Makarov, John Alec Moral, Romain Remark, Brian Herbst, Gokce Askan, Umesh Bhanot, Yasin Senbabaoglu, Daniel K. Wells, Charles Ian Ormsby Cary, Olivera Grbovic-Huezo, Marc Attiyeh, Benjamin Medina, Jennifer Zhang, Jennifer Loo, Joseph Saglimbeni, Mohsen Abu-Akeel, Roberta Zappasodi, Nadeem Riaz, Martin Smoragiewicz, Z. Larkin Kelley, Olca Basturk, Mithat Gönen, Arnold J. Levine, Peter J. Allen, Douglas T. Fearon, Miriam Merad, Sacha Gnjatic, Christine A. Iacobuzio-Donahue, Jedd D. Wolchok, Ronald P. DeMatteo, Timothy A. Chan, Benjamin D. Greenbaum, Taha Merghoub, Steven D. Leach (2017). Identification of unique neoantigen qualities in long-term survivors of pancreatic cancer
- (2021). How to turn up the heat on the cold immune microenvironment of metastatic prostate cancer.
- Jérôme Galon, Daniela Bruni (2019). Approaches to treat immune hot, altered and cold tumours with combination immunotherapies
- Mikhail Binnewies, Edward W. Roberts, Kelly Kersten, Vincent Chan, Douglas F. Fearon, Miriam Merad, Lisa M. Coussens, Dmitry I. Gabrilovich, Suzanne Ostrand-Rosenberg, Catherine C. Hedrick, Robert H. Vonderheide, Mikael J. Pittet, Rakesh K. Jain, Weiping Zou, T. Kevin Howcroft, Elisa C. Woodhouse, Robert A. Weinberg, Matthew F. Krummel (2018). Understanding the tumor immune microenvironment (TIME) for effective therapy
- Priti S. Hegde, Daniel S. Chen (2020). Top 10 Challenges in Cancer Immunotherapy
Team Review: This article has been reviewed by Canceria Research Team